
Medication management for seniors: who does what
Older adults make over 600,000 ER visits a year for medication problems. How to set up safe medication management for a parent, and who handles each part.
Published Updated

Older adults visit the emergency room more than 600,000 times a year because of problems with their medicines, more than twice as often as younger people, according to the CDC. Most of those visits don't involve rare drugs or strange reactions. They involve ordinary medicines taken in the wrong combination, the wrong amount or at the wrong time.
Good medication management for seniors is mostly organization: one current list, one pharmacy, one pill organizer, one daily routine, and a clear sense of who is responsible for each part. When everyone assumes someone else is watching, no one is. Here is how to divide the work, and where a little daily help matters most. None of it replaces your parent's pharmacist or doctor, who are part of the plan.
How many medicines older adults take
The American Geriatrics Society notes that more than 90% of older adults use at least one prescription medicine and more than two-thirds use three or more in a given month. The share of Americans 65 and older taking five or more prescription drugs, a level usually called polypharmacy, rose from about 24% in 1999 to 2000 to 39% in 2011 to 2012.
Those medicines are a big reason people live longer. But each one adds a chance for an interaction, a duplicate or a missed dose, and older bodies take the consequences harder. A national study of emergency hospitalizations for drug reactions in older Americans, published in the New England Journal of Medicine in 2011, found that about two-thirds involved just four kinds of medicine: blood thinners such as warfarin, insulin, antiplatelet drugs and diabetes pills. Nearly half of the patients were 80 or older.
Who does what
Write down who owns each part of the job. This is the division of labor that keeps a routine safe:
- The prescribers decide what to start, the dose, and what to reduce or stop (called deprescribing). They can't see what other doctors prescribed, or how the day really goes at home, unless someone tells them.
- The pharmacist checks the full list for interactions and duplicates, answers "is this safe with that," and can line up refills on one date. They can't catch a conflict with a drug filled at another pharmacy.
- Your parent takes each dose and says how they feel. They can't always remember every dose, or notice their own subtle side effects.
- The family keeps the master list current, fills the organizer (or has the pharmacy do it) and books the reviews. They can't be there for every dose.
- A home caregiver reminds at each dose from the filled organizer, sees that it's taken and reports anything that seems off. They don't choose, measure, change or decide on any medicine.
That last part is the most misunderstood. A non-medical caregiver isn't a nurse. The job is reminders and a second set of eyes, not dosing. Keep that line clear and the rest of the system works.
One list and one pharmacy
Everything starts with a written list of every prescription, over-the-counter medicine, vitamin and supplement, with the dose, the schedule, the prescriber and the reason for each. The FDA suggests keeping one copy at home and one in a wallet or phone, and showing it at every appointment, including the dentist. Over-the-counter products belong on it too; a daily pain reliever or antacid can interact with prescriptions. Our guide to taking acetaminophen safely explains one common example.
Then fill everything at one pharmacy, so one pharmacist can check the whole list. Once or twice a year, put every bottle in a bag and bring it in for a review, often called a brown-bag review. MedlinePlus recommends using one regular pharmacist and bringing medicines in their original bottles. Many pharmacies can also synchronize refills so they all come due on the same day each month.
An organizer your parent will actually use
The pill organizer is the workhorse of medication safety at home, but only if it fits the person. Weekly organizers come with one to four compartments a day for morning, noon, evening and bedtime. Automatic dispensers hold weeks of pills, open on a schedule and sound an alarm when it's time.
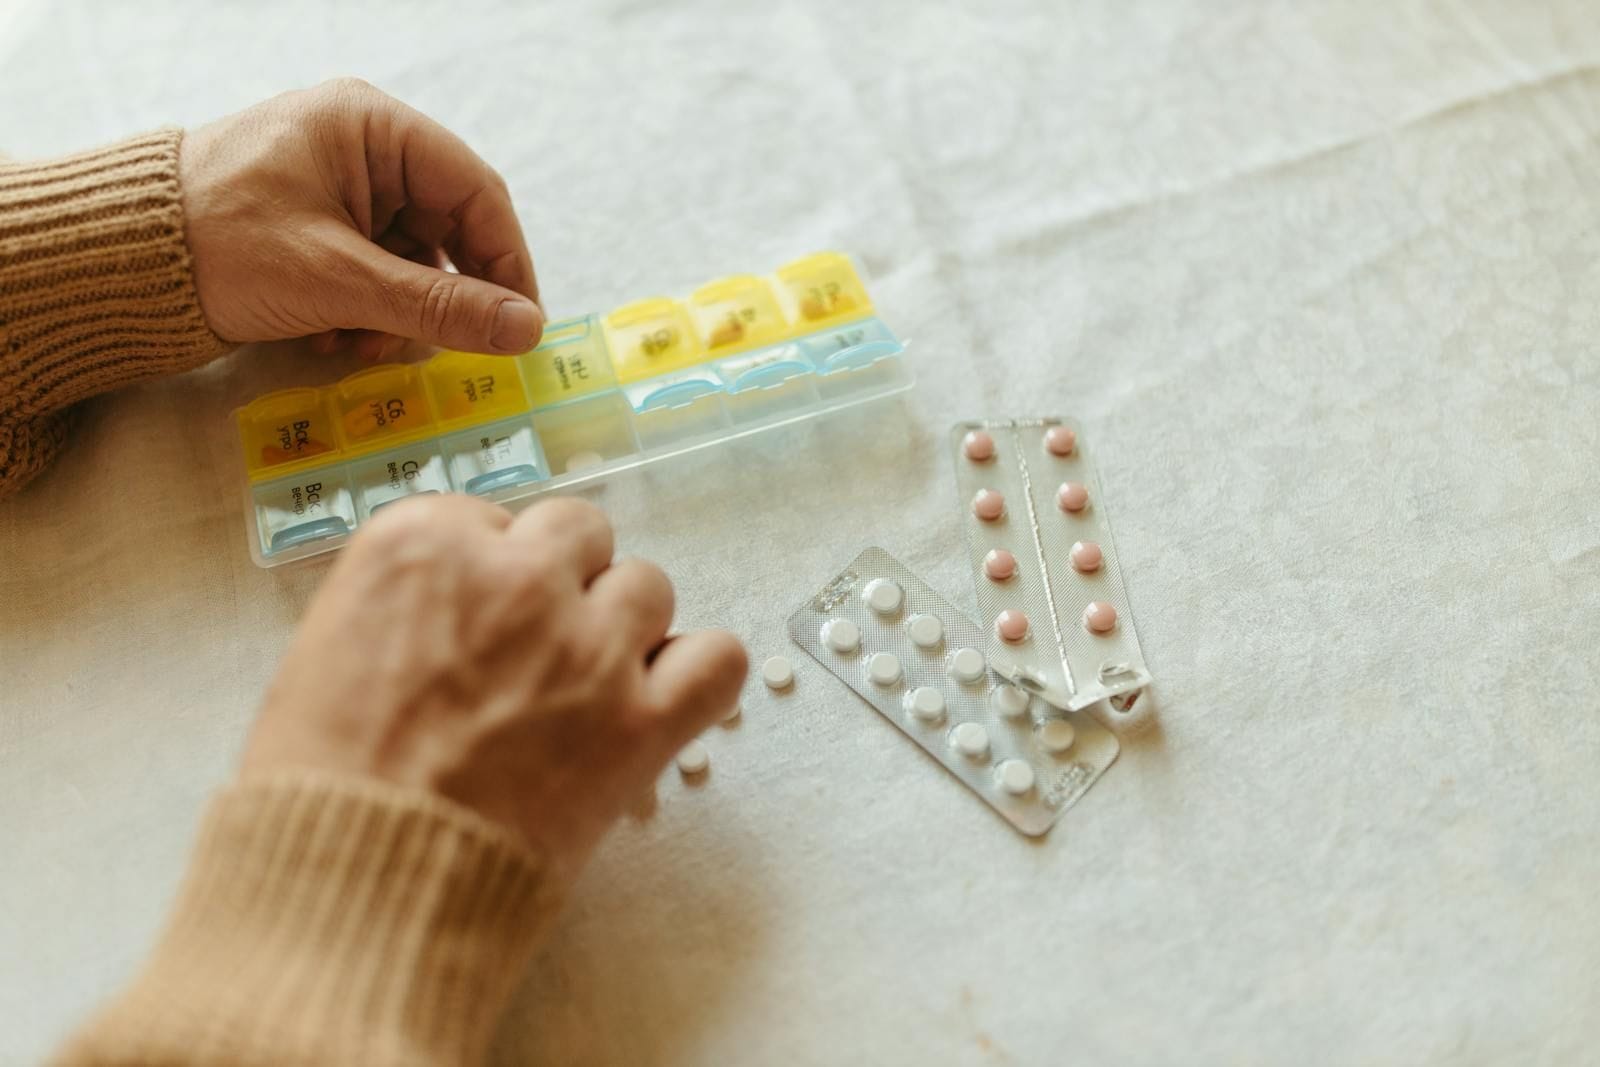
Choose one your parent can open and read. Stiff fingers and child-resistant lids don't mix, so ask the pharmacist for easy-open caps. Weak eyes need large, high-contrast labels. And decide who fills it: the family or the pharmacy, working from the master list. A caregiver who later gives the reminders shouldn't be the one deciding what goes in.
Tie every dose to something that already happens
A box doesn't take pills; a routine does. Attach each dose to something that happens at the same time every day: breakfast, brushing teeth, the evening news. The World Health Organization has long reported that people take only about half of their long-term medicines as prescribed, and forgetting is one of the most common reasons. It isn't a character flaw. It's what happens when a complicated schedule meets a busy day or a fading memory.
This is the gap a present person fills. A spouse, an adult child or a caregiver who offers the dose on time, sees it taken and notices when something seems off turns a filled organizer into doses actually taken. Medication reminders are a standard part of our personal care and companion care. The caregiver doesn't decide anything. They make the routine happen, the same way, every day.
The riskiest week is the one after the hospital
Medication routines fall apart most often at transitions: a hospital discharge, a move home from rehab, a new specialist. Doses change, new drugs appear, old ones stop, and the old bottles are still in the cabinet. The Agency for Healthcare Research and Quality notes that medications are behind many of the problems patients have after discharge.
That week, compare the discharge list line by line against the old list, ideally with the pharmacist. Remove anything that was stopped from the organizer and the cabinet. Ask which new medicine treats what. Our hospital-to-home care puts a caregiver in the house for those first days, when the routine is new.
Some conditions make timing especially important. Parkinson's medicines work in a tight window, and a late dose can mean stiffness, slowness and a higher risk of falling. Our Parkinson's care builds the day around the dose schedule.
What a second set of eyes catches
Older adults often can't report the side effects that matter most, because they look like aging: new confusion, dizziness, a fall, poor appetite, bad sleep, a new tremor. The Family Caregiver Alliance lists dizziness, confusion, delirium, insomnia, Parkinson's-like symptoms, loss of appetite, falls and memory changes as signs a dose may be too high. None of them announces itself as a medication problem, which is why someone who sees your parent regularly is the early warning.

When something looks wrong, the answer is to ask, not to adjust. No one at home should stop or change a medicine on their own.
- A question about an interaction or a new symptom: call the pharmacist.
- A symptom that may need a dose change: call the prescriber.
- Trouble breathing, swelling of the face or throat, collapse, a seizure, or someone who can't be woken: call 911.
Sudden confusion deserves a same-day call rather than a shrug. A fast change in thinking is often the first sign that something, sometimes a medicine, is wrong.
When cost quietly breaks the routine
Some missed doses have nothing to do with memory. Older adults sometimes skip doses or stretch a prescription to save money, and they rarely say so. If you suspect it, ask gently, then bring it to the pharmacist or prescriber, who can often find a generic or a lower-cost alternative. Medicare beneficiaries can also ask about Extra Help with Part D costs through Social Security. Stretching a medicine to make it last is a safety risk.
Storage and disposal
Keep medicines in a cool, dry place, not a steamy bathroom cabinet, and out of reach of visiting grandchildren and pets. The National Institute on Aging advises keeping opioid pain medicines locked up.
Clear out expired and discontinued medicines, which removes the look-alikes behind many mix-ups. The FDA says take-back programs are the best way to dispose of most unused medicines. Many pharmacies and police stations have drop-off kiosks, and the DEA holds national take-back days.
Where to start this week
- Write the list: every medicine and supplement, the dose and the reason.
- Move every prescription to one pharmacy and ask for a review.
- Choose an organizer your parent can open and read, and fill it on a set day.
- Tie each dose to something that already happens every day.
- Decide who does the daily reminder, and who they call when something seems off.
The daily reminder and the watchful eye are the parts most often left to chance. If no one in the family can be there at pill time, our caregivers can. Call us or request care, and we'll build medication reminders into the visit schedule.
Common questions
Click or tap a question to see the answer.
What is medication management for the elderly?
Medication management is the everyday system that keeps an older adult taking the right medicines, in the right amounts, at the right times, without dangerous overlaps or missed doses. It involves the prescribers who decide what to take, a pharmacist who checks the full list for interactions, the person taking the medicines, the family who keeps the list current and fills the organizer, and anyone who helps with daily reminders.
What is polypharmacy, and why is it a concern?
Polypharmacy usually means regularly taking five or more medicines at once. It matters because each added medicine is another chance for an interaction, a duplicate, a side effect or a mix-up in the schedule. A national study found the share of Americans 65 and older taking five or more prescription drugs rose from about 24% in 1999 to 2000 to 39% in 2011 to 2012. Polypharmacy isn't automatically wrong, but it's a good reason to ask the doctor and pharmacist whether every medicine is still needed.
Can a home care caregiver give an elderly person their medication?
A non-medical home caregiver provides medication reminders: they prompt the person to take each dose from an organizer that the family or pharmacist has already filled, see that it's taken, and report concerns to the family. They don't choose, measure or change doses, and they don't give injections, which are skilled nursing tasks. Deciding what goes in the organizer stays with the prescriber, the pharmacist and the family.
How do I organize an elderly parent's medications?
Make one written list of every prescription, over-the-counter medicine, vitamin and supplement, with the dose, schedule and reason for each. Fill everything at one pharmacy and ask the pharmacist to review the whole list. Choose a pill organizer your parent can open and read, fill it on the same day each week, and tie each dose to something that already happens, such as breakfast or brushing teeth. Update the list after every appointment and hospital stay.
What are signs that a medication dose may be too high in an older adult?
The Family Caregiver Alliance lists dizziness, confusion, delirium, trouble sleeping, Parkinson's-like symptoms such as shakiness or stiffness, loss of appetite, falls and changes in memory as possible signs that a dose is too high. These are easy to mistake for normal aging. Report any new or worsening symptom after a medication change to the pharmacist or prescriber promptly, and don't stop or change a medicine on your own.
What is the safest way to dispose of unused medications?
The U.S. Food and Drug Administration says drug take-back options are the best way to get rid of most unused or expired medicines, including opioids and other controlled substances. Many pharmacies, hospitals and police stations have take-back kiosks, and the DEA holds National Prescription Drug Take Back Days. Prepaid mail-back envelopes are another option. Clearing out old medicines also removes the look-alikes that cause mix-ups at home.



